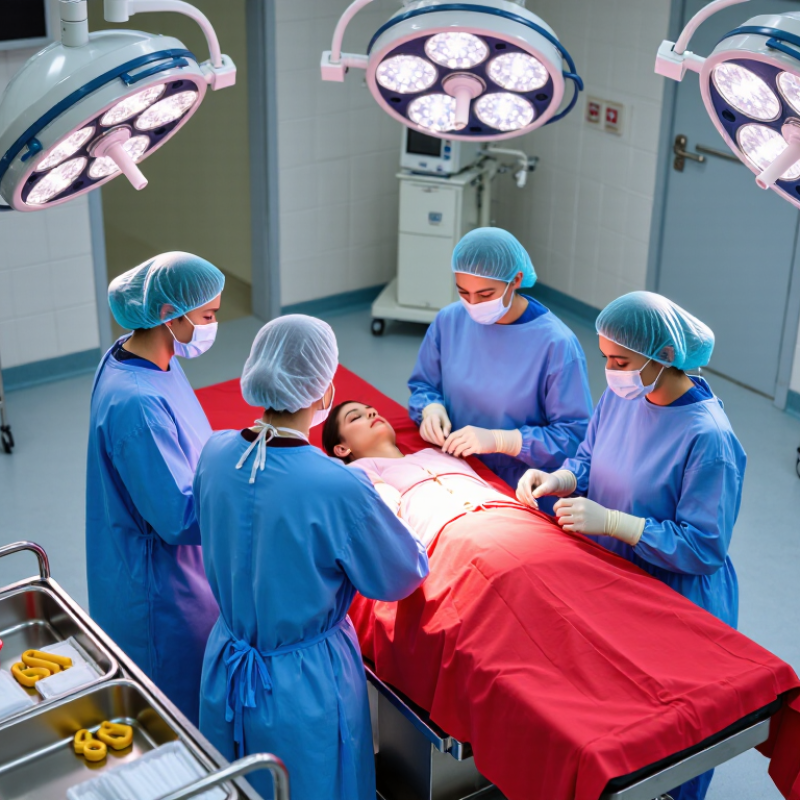
What Is CRI and How Does It Affect Surgery? The question matters under bright operating-room lights, where clinicians assess tissue color, blood, and subtle changes around an incision. Color rendering index, or CRI, estimates how accurately a light source reveals colors compared with a reference source. A higher score can indicate more faithful color appearance. It does not guarantee that every important shade will look natural.
How does color rendering index (CRI) affect surgery? In practical terms, surgical lighting with strong color rendering can help clinicians distinguish visual details. But CRI is only one measure. It does not fully describe a light’s spectrum, brightness, glare, shadows, or how specific reds appear. Lighting researcher Kevin Houser’s work on color quality supports a careful interpretation; a paraphrase of the relevant principle is: “CRI is useful, but it cannot describe every aspect of color appearance.” This is not a substitute for a verified direct quotation.
That distinction matters. A lamp can score well on CRI yet still render some clinical colors less clearly than expected. Think of a red surgical drape beside a pale tissue surface: both may appear different under another light source. That sounds simple. It isn’t. This introduction explores what CRI measures, where the metric falls short, and why surgical teams consider lighting alongside other design and clinical requirements. No single score can establish that a light is suitable for every procedure. Specific needs vary, and lighting decisions should rely on appropriate technical standards and qualified clinical and engineering guidance.
Chronic renal insufficiency (CRI) describes a lasting reduction in kidney function. Clinicians now commonly use the term chronic kidney disease (CKD). The condition is generally identified when kidney damage or reduced function persists for at least three months. It is not diagnosed from one unusual test result.
Doctors estimate kidney function using blood creatinine levels and the estimated glomerular filtration rate, or eGFR. An eGFR below 60 over three months or longer can indicate CKD. Other clues include albumin, a type of protein, in the urine. Blood pressure readings, medical history, and repeat tests help clarify what the numbers mean. One result alone can mislead.
CRI can range from mild impairment to advanced loss of function. Early on, many people notice no symptoms. That can feel confusing. A clinician may review trends in lab results, urine tests, and medications rather than rely on a single appointment. The term “insufficiency” also sounds more definite than the situation may be; kidney function and risk differ from person to person. A careful definition helps patients understand what is known, and what still needs checking.
Chronic renal insufficiency, often called chronic kidney disease, means kidney damage or reduced function lasting at least three months. Diabetes and high blood pressure are common causes. They can gradually injure the tiny filtering vessels, sometimes without obvious symptoms. Other causes include inflammation of the kidney’s filtering units, inherited conditions, and long-term urinary blockage. Some medicines can also worsen kidney function, especially when used without medical guidance. The cause is not always clear. That uncertainty matters when clinicians plan care around surgery.
Doctors classify kidney function using estimated glomerular filtration rate, or eGFR, alongside urine albumin and other findings. Stages G1 and G2 indicate eGFR of 90 or higher, or 60–89, but require evidence of kidney damage to count as chronic kidney disease. G3a is 45–59; G3b, 30–44; G4, 15–29; and G5, below 15. These numbers describe function, not how a person feels. Quiet disease is possible. For surgical planning, the stage can help clinicians assess fluid balance, medication choices, and recovery risks. It does not predict an individual outcome by itself; recent lab results and the reason for kidney disease also matter.
Chronic renal insufficiency (CRI) can change how the body handles anesthesia, medicines, and fluid shifts during surgery. Reduced kidney function may also mean anemia or abnormal potassium levels, which can strain the heart and complicate recovery. A 2013 JAMA analysis of more than 2.4 million noncardiac surgical patients found that those with an estimated glomerular filtration rate below 30 had about 2.8 times the adjusted odds of 30-day death compared with patients whose kidney function was normal. That figure describes a group, not an individual’s outcome. The study also cannot represent every operation or patient.
After surgery, teams may monitor creatinine, potassium, blood pressure, and urine output more closely. A sudden drop in urine, new swelling, or rising creatinine can signal acute kidney injury. CRI can make this harder to manage because some pain medicines and antibiotics remain in the body longer, while excess fluids may worsen swelling or breathlessness. Recovery may take longer, especially when kidney function is severely reduced or dialysis is needed. Not every patient follows that pattern. That uncertainty matters. Before surgery, patients should share their medication list and recent kidney test results; clinicians can then adjust drug doses, fluid plans, and follow-up around the person’s actual kidney function.
Estimated glomerular filtration rate (eGFR) categories used to assess kidney function before surgery
Chronic renal insufficiency (CRI), often discussed as chronic kidney disease (CKD), can reduce the kidneys’ ability to handle medicines, fluids, and electrolytes. Lower eGFR may therefore affect surgical planning and recovery, but this chart shows kidney-function categories—not a person’s individual surgical risk. CKD diagnosis also depends on evidence of kidney abnormality lasting at least three months; eGFR alone does not establish CKD in categories G1 or G2.
eGFR in mL/min/1.73 m². G1 is shown from 90 to 120 for display; G5 means below 15. Categories follow KDIGO eGFR classification.
Chronic renal insufficiency (CRI) can affect how the body handles fluids, medicines, and surgical stress. Preoperative assessment should begin with the patient’s usual kidney function, not just one test result. Clinicians review recent creatinine and estimated filtration rate, compare them with earlier results, and check electrolytes, especially potassium. They also ask about urine changes, swelling, fatigue, and any recent illness. Small details matter.
Medication review is essential. Some pain relievers and other medicines can strain the kidneys or build up when kidney function is reduced. The care team should check prescriptions, nonprescription drugs, and supplements, then decide whether any changes are appropriate. Patients should not stop prescribed medicines on their own. Blood pressure and fluid status also need attention; ankle swelling, shortness of breath, or signs of dehydration may change the plan.
For patients receiving dialysis, the surgical and kidney teams coordinate treatment timing and review access sites and recent laboratory results. Anesthesia planning may also account for anemia, electrolyte changes, and slower drug clearance. A single reassuring lab value can hide a worsening trend, so it should not tell the whole story. Assessment is individualized, and uncertainty should be discussed openly with the clinicians involved.
Chronic renal insufficiency (CRI), often described as chronic kidney disease, can change how the body handles medicines, fluids, and anesthesia. The CDC’s 2023 chronic kidney disease fact sheet estimates that about 1 in 7 U.S. adults has CKD, while roughly 9 in 10 are unaware. Before surgery, clinicians should review kidney function, recent creatinine and estimated filtration rate, blood pressure, and all medicines, including over-the-counter pain relievers. The 2024 AHA/ACC perioperative guideline supports structured cardiovascular risk assessment; kidney disease is one factor that may shape the plan. Small changes matter.
Care should be tailored, not automatic. The surgical and anesthesia teams can coordinate with the patient’s kidney specialist when disease is advanced or function is changing. They may adjust medicine doses, avoid unnecessary kidney-stressing drugs, and plan fluid management around the patient’s heart and kidney status. Too little fluid can impair circulation; too much can cause swelling or breathing problems. That balance is difficult.
After surgery, track urine output, blood pressure, fluid balance, and repeat kidney tests when clinically appropriate. Explain which medicines to continue or pause, and when to seek help for reduced urination, worsening swelling, or vomiting. KDIGO’s 2024 CKD guideline emphasizes monitoring kidney function and reviewing medicines as part of ongoing care. A checklist helps, but it cannot replace judgment; risk estimates are imperfect, and recovery does not always follow the plan.
| Dimension | Evidence-Based Information | Perioperative Relevance | Care and Risk-Reduction Considerations |
|---|---|---|---|
| Meaning of CRI | Chronic renal insufficiency (CRI) is commonly used to describe long-term reduced kidney function. Current clinical guidelines generally use the term chronic kidney disease (CKD), defined by kidney abnormalities lasting at least 3 months. | Reduced kidney function can affect fluid balance, electrolyte regulation, medication clearance, and the body’s response to surgical stress. | Review the patient’s kidney history and results over time; do not interpret one abnormal test alone as proof of chronic disease. |
| CKD stages by eGFR |
G1: at least 90 mL/min/1.73 m² G2: 60–89 mL/min/1.73 m² G3a: 45–59 mL/min/1.73 m² G3b: 30–44 mL/min/1.73 m² G4: 15–29 mL/min/1.73 m² G5: below 15 mL/min/1.73 m² |
Risk generally increases as kidney function declines, but eGFR alone does not determine surgical risk. G1 or G2 indicates CKD only when other evidence of kidney damage is present. | Use eGFR alongside urine albumin, the cause and stability of CKD, comorbidities, planned procedure, and overall clinical condition. |
| Acute kidney injury (AKI) | AKI is a sudden decline in kidney function and is distinct from chronic kidney disease, although a patient with CKD may also develop AKI. | Surgery, infection, blood loss, low blood pressure, dehydration, or medication effects may contribute to perioperative kidney injury. | Document baseline creatinine and eGFR, maintain appropriate circulation and fluid balance, and monitor kidney function when clinically indicated. |
| Fluid balance and blood pressure | Kidneys help regulate water and sodium balance. CKD can make patients more susceptible to fluid overload or volume depletion, depending on their condition and treatment. | Both inadequate circulation and excess fluid may complicate anesthesia and recovery. | Assess volume status and blood pressure before and after surgery. Individualize fluid and blood-pressure management; avoid assuming that one fluid strategy is suitable for every patient. |
| Electrolytes and acid–base balance | Advanced CKD may be associated with abnormalities such as elevated potassium, reduced bicarbonate, or disturbances in other electrolytes. | Significant abnormalities can affect heart rhythm, muscle function, and anesthesia planning. | Review recent laboratory results and correct clinically important abnormalities before elective procedures when feasible. Repeat testing according to the patient’s condition and procedure. |
| Medication clearance | Some medicines or their active metabolites are cleared partly or primarily by the kidneys. Reduced kidney function can increase exposure and adverse-effect risk. | Medication effects may last longer, and standard doses may not be appropriate for every patient with reduced eGFR. | Reconcile prescription and non-prescription medicines; check kidney-function guidance for drug selection and dosing. Review perioperative medication changes individually with the treating team. |
| Nephrotoxic exposures | Some exposures, including non-steroidal anti-inflammatory drugs (NSAIDs) and certain contrast-related or antimicrobial treatments, may pose kidney risks in susceptible patients. | Risk depends on the patient’s kidney function, other illnesses, dose, duration, and clinical circumstances. | Review whether potentially nephrotoxic medicines or exposures are necessary, consider safer alternatives when appropriate, and monitor kidney function based on clinical risk. |
| Anemia and bleeding considerations | CKD may be associated with anemia. Advanced kidney disease can also affect platelet function, while many patients have additional bleeding or clotting risks. | Anemia may reduce tolerance of blood loss; bleeding and thrombosis planning may be more complex, particularly for patients taking anticoagulants or receiving dialysis. | Assess blood count and bleeding history when relevant. Coordinate decisions about anticoagulants, antiplatelet medicines, and dialysis-related anticoagulation with the appropriate clinicians. |
| Dialysis and access planning | Some people with advanced CKD receive hemodialysis or peritoneal dialysis. Dialysis timing and prescription are individualized. | Electrolytes, fluid status, dialysis access, and anticoagulation may affect anesthesia and procedural planning. | Coordinate with the nephrology and dialysis teams. Confirm the dialysis plan and protect the patient’s vascular access; do not use a fixed timing plan without individual assessment. |
| Postoperative monitoring | After surgery, kidney function may be affected by hemodynamic changes, fluid shifts, infection, blood loss, and medication exposure. | Early recognition of worsening kidney function or fluid and electrolyte problems may support timely treatment. | Monitor clinical status, urine output when appropriate, and laboratory results according to the patient’s risk and procedure. Review medicines and avoid unnecessary kidney stressors during recovery. |
| Individualized risk assessment | CRI/CKD does not automatically prevent surgery. The level of risk depends on kidney function, disease stability, other medical conditions, and the type and urgency of the procedure. | Elective and urgent procedures may require different preparation and monitoring. | Use shared planning among the patient, surgeon, anesthesiology team, and nephrology team when appropriate. Balance potential surgical benefit against the patient-specific risks. |
Note: This table provides general educational information, not individualized medical advice. CKD staging categories are based on estimated glomerular filtration rate (eGFR); a CKD diagnosis requires evidence of chronicity, and treatment decisions should be made by the patient’s healthcare team.
Chronic kidney problems can affect fluid balance, medicine clearance, and responses to anesthesia. Clinicians compare recent kidney tests with earlier results. One test alone may miss a changing trend.
They may check creatinine, estimated kidney filtration, and electrolytes such as potassium. They may also ask about urine changes, fatigue, swelling, or recent illness. Small details matter.
The care team reviews prescriptions, pain relievers, and supplements. Some medicines may need adjustment, but patients should not stop prescribed drugs on their own. Ask the clinician handling your care.
Too little fluid may reduce circulation, while too much can worsen swelling or breathing. Ankle swelling, shortness of breath, and dehydration signs may influence decisions. The balance is not always simple.
The surgical and kidney teams can coordinate dialysis timing and review access sites and recent test results. Timing may vary. It should be discussed with the care team.
Anemia, electrolyte changes, and slower medicine clearance may shape anesthesia planning. Clinicians may adjust doses or avoid unnecessary kidney-stressing medicines. Individual responses can differ.
Clinicians may track urine output, blood pressure, fluid balance, and repeat kidney tests when appropriate. Patients should ask which medicines to continue or pause. A checklist helps, but it is not a guarantee.
Contact the care team about reduced urination, worsening swelling, or vomiting. These symptoms deserve attention. Recovery may not follow the expected plan.
Chronic renal insufficiency (CRI) is a long-term decline in kidney function that can affect how the body balances fluids, removes waste, and processes medicines. Its causes may include diabetes, high blood pressure, and other kidney disorders. CRI is commonly described in stages according to the degree of reduced kidney function, and the stage helps clinicians understand a patient’s health needs.
Before surgery, CRI may increase the risk of fluid or electrolyte imbalances, medication-related complications, and slower recovery. Preoperative assessment typically considers kidney function, other medical conditions, current medicines, and the planned procedure. During and after surgery, the care team can reduce risks by adjusting medication choices and doses, monitoring fluid balance and kidney function, and planning appropriate follow-up. The phrase “How does color rendering index (CRI) affect surgery?” uses the same abbreviation, but here CRI refers to chronic renal insufficiency, not color rendering index.
Emfix Medical